Quick answer
Cervical instability means ligaments holding the upper neck and skull together are too lax to keep the head aligned. It is common in Ehlers-Danlos and after whiplash, and can cause brain fog, dizziness, ear rushing and migraines. Dr. Tortland confirms it with digital motion X-ray and diagnostic injections, then treats with prolotherapy and custom-concentrated PRP.
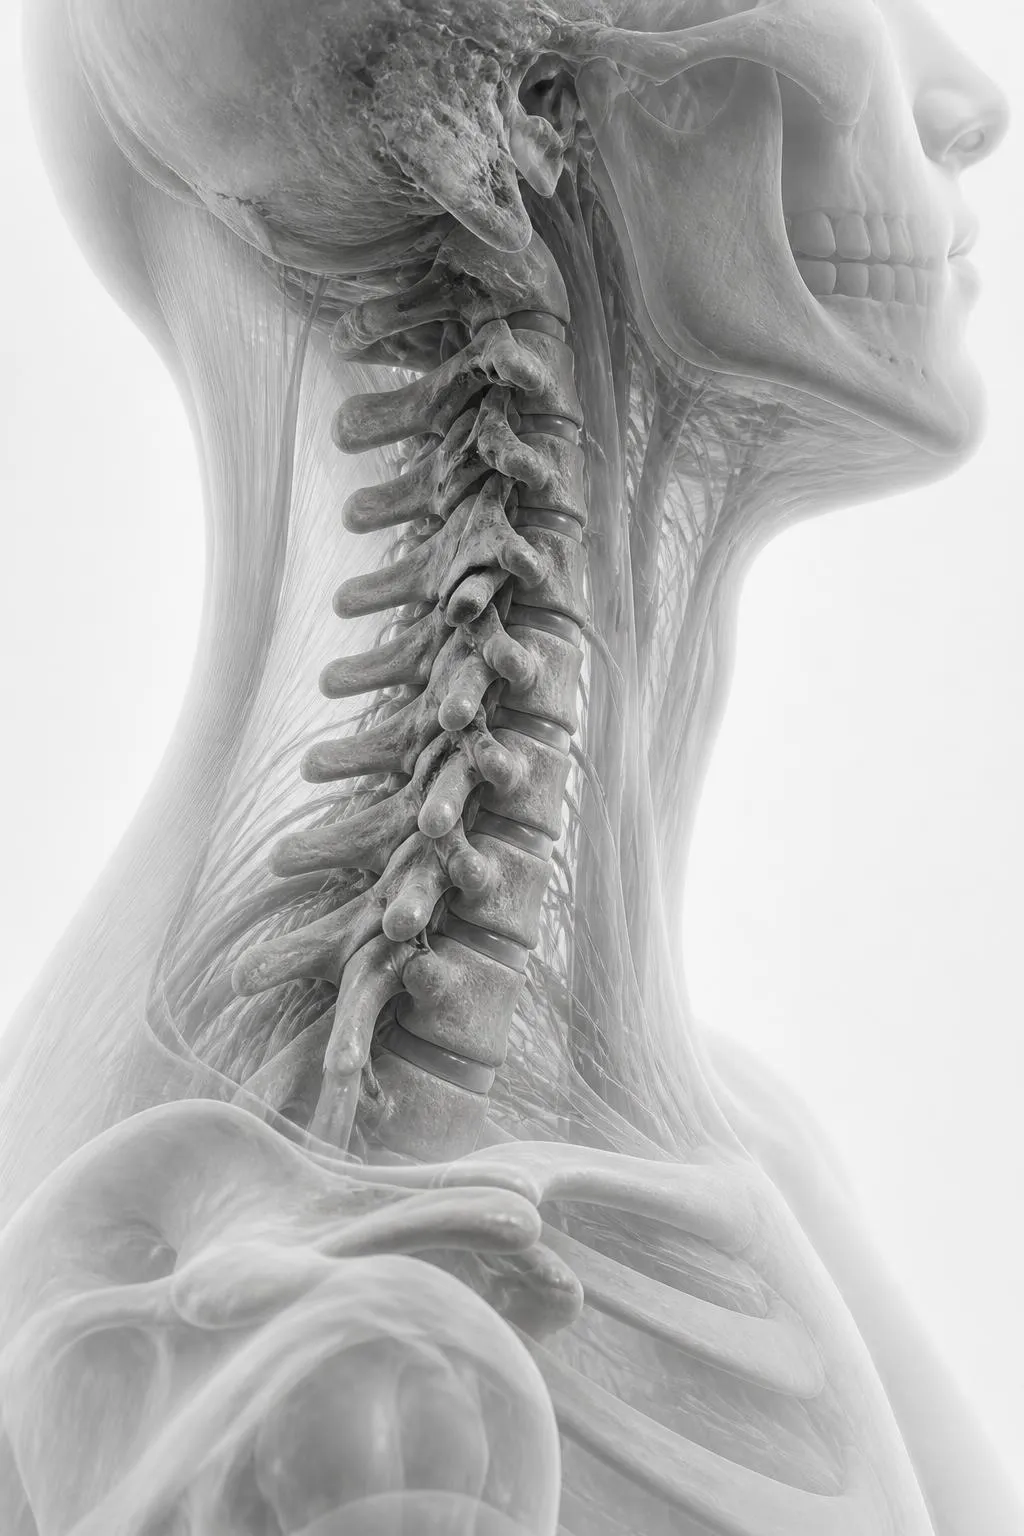
Associated conditions
EDS, generalized hypermobility, nerve entrapment, vagus nerve compression, TMJ dysfunction, Eagle's syndrome
Diagnosis method
Digital motion X-ray (DMX) and diagnostic injections to the cervical facet ligaments
Interventional options
Diagnostic facet ligament injections, nerve hydrodissection
First visit
At least an hour, $500 in the office (ultrasound included) or $300 by telehealth
Physician
Paul Tortland, DO, FAOASM, CAQSM, RMSK
Who treats you
Dr. Tortland personally, every visit
Main treatments
Prolotherapy and custom-concentrated PRP to tighten and strengthen the lax ligaments
Payment
Out of network and direct pay; HSA / FSA eligible
When to see a doctor
When to seek an evaluation
Consider an evaluation if you have unexplained brain fog, dizziness or vertigo, a rushing or pulsing sound in one or both ears, chronic neck or shoulder pain, TMJ or jaw pain, migraines, light sensitivity, or a head that feels heavy or hard to hold up, especially alongside joint hypermobility, a diagnosis of EDS, or a history of whiplash, concussion, or other head or neck trauma.
Seek emergency care right away, not an office visit, for sudden severe headache unlike any before, new weakness or numbness in an arm or leg, loss of coordination, difficulty swallowing or speaking, or neck pain after a significant fall or high-speed accident.
The challenge with cervical instability is that its symptoms overlap heavily with anxiety, vestibular disorders, and primary headache conditions, so it is frequently missed or misattributed. A standard cervical MRI or static X-ray usually looks normal because it captures the neck in one fixed position; instability by definition only shows itself with motion or stress on the ligaments, which is why the diagnostic approach matters as much as the treatment.
Related conditions
Conditions and symptoms linked to instability
Cervical ligament laxity is frequently connected to, or mistaken for, the conditions below.
Diagnose · Confirm · Treat
How Dr. Tortland evaluates instability
Diagnose the instability with motion, confirm the ligament as the source with an injection, then treat what is actually lax.
01
History, exam and symptom mapping
An unrushed first visit maps your full symptom pattern, including brain fog, dizziness, ear rushing, neck and shoulder pain, TMJ or jaw pain, migraines, light sensitivity, and head heaviness, against your history of hypermobility, EDS, or prior head or neck trauma.
02
Digital motion X-ray (DMX)
DMX captures the cervical spine in flexion, extension and rotation to reveal instability that a static MRI or X-ray, taken in one fixed position, cannot show.
03
Diagnostic injections to the cervical facet ligaments
A small volume of anesthetic placed at the suspected lax ligament confirms it as the true source of your symptoms before treatment begins, the same validate-before-treat approach used throughout this practice.
04
Nerve hydrodissection
When lax ligaments are irritating or entrapping a nearby nerve, or contributing to vagus nerve compression, ultrasound-guided hydrodissection frees the nerve from surrounding tissue.
05
Prolotherapy
A dextrose solution is injected into the lax cervical ligaments to stimulate a localized healing and tightening response, the traditional first-line regenerative treatment for ligament laxity.
06
Custom-concentrated PRP
For ligaments that need a stronger biologic signal, PRP is custom-prepared on site to 12 to 15 times baseline platelet concentration and placed directly into the lax ligament under ultrasound guidance.
07
Follow-up and re-evaluate
Follow-up at six to ten weeks compares your symptoms against baseline; most patients need a short series of injections spaced several weeks apart as the ligament tightens.
Candidacy
Who it helps and when specialist care is needed
Comparison
Treatment options compared
| Option | What it does | Duration of benefit | Effect on tissue |
|---|---|---|---|
| Cervical collar / physical therapy | Supports the neck and builds deep neck flexor strength to reduce load on lax ligaments | Ongoing; depends on continued use and exercise | No direct ligament repair; foundational, not definitive |
| Diagnostic facet ligament injection | Anesthetic at a specific cervical ligament to confirm it as the symptom source | Hours; diagnostic, not a treatment | No lasting tissue effect; confirms the diagnosis |
| Prolotherapy | Dextrose solution into lax cervical ligaments to stimulate a localized tightening response | Cumulative over a short series of visits | Aims to tighten and strengthen ligament tissue |
| Custom-concentrated PRP | Delivers a high concentration of growth factors into the lax ligament to stimulate repair | Commonly building over months, per course | Aims to improve ligament quality and strength |
| Cervical fusion surgery | Surgically stabilizes the craniocervical junction or cervical spine | Long-term, definitive for true structural instability | Structural change with recovery cost; reserved for frank instability with neurologic compromise |
Frequently asked
Cervical instability questions
What is cervical instability?
Why do I have brain fog, dizziness, and ear rushing if this is a neck problem?
How is cervical instability diagnosed if my MRI looks normal?
What is a digital motion X-ray (DMX)?
Is cervical instability connected to EDS and hypermobility?
What is nerve hydrodissection, and why would I need it for a neck problem?
What is prolotherapy, and how is it different from PRP?
Does insurance cover cervical instability treatment, and what does it cost?
Who performs my cervical injections?
Sources
Instability evidence and further reading
01
Mulvaney SW, Tortland PD, Shiple B, Curtis K. Regenerative medicine options for chronic musculoskeletal conditions: a review of the literature. Endurance and Sports Medicine. 2018.
02
Henderson FC Sr, Austin C, Benzel E, et al. Neurological and spinal manifestations of the Ehlers-Danlos syndromes. Am J Med Genet C Semin Med Genet. 2017;175(1):195-211.
03
Dagenais S, Yelland MJ, Del Mar C, Schoene ML. Prolotherapy injections for chronic low-back pain. Cochrane Database Syst Rev. 2007;(2):CD004059.
05
Maniquis-Smigel L, Reeves KD, et al. Short term analgesic effects of 5% dextrose epidural injections for chronic low back pain: a randomized controlled trial. Anesth Pain Med. 2016;7(1):e42550.