Where to See Dr. Tortland in Connecticut
Dr. Paul Tortland, DO provides comprehensive orthopedic evaluations for patients at his Glastonbury, CT office. The practice sees patients from Glastonbury, Hartford, West Hartford, Farmington, Simsbury, South Windsor, and other Connecticut and New England communities.
📍 59 Sycamore Street, Suite 301, Glastonbury, CT 06033 — Get directions
📞 (860) 430-2821
Learn more about Dr. Tortland · Request an evaluation
Why the Spine Is a Different Category
Most patients who ask about PRP are thinking about joints — a knee, a shoulder, a hip. The lumbar spine is a legitimate and increasingly studied target for orthobiologic treatments, but it presents a different set of technical demands than a large peripheral joint. The structures involved are smaller, deeper, and more closely adjacent to anatomy that requires precise avoidance. This is not a setting where anatomical estimation or surface landmarks alone are sufficient.
What separates a clinically appropriate spinal PRP procedure from an inadvisable one is primarily technique — specifically, whether real-time imaging guidance is used, and whether the practitioner has the subspecialty training to interpret what they're seeing and adjust needle position accordingly.
What a Lumbar Spine PRP Procedure Actually Targets
The lumbar spine contains several distinct structures that can be sources of chronic pain and that may be appropriate targets for regenerative treatment, depending on diagnosis:
Facet joints — small paired joints along the back of each lumbar vertebra, which can become arthritic and generate significant local and referred pain. The facet joint capsule is a discrete anatomical target accessible under ultrasound.
Medial branch nerves — the nerves that supply sensation to the facet joints. Targeting these nerves with regenerative rather than destructive treatment is an approach distinct from conventional medial branch blocks or radiofrequency ablation.
The transverse process — a bony landmark of the vertebra used for orientation and as a reference point for needle positioning.
The lamina and multifidus — the lamina is the posterior bony arch of the vertebra; the multifidus is the deep paraspinal muscle overlying it, which plays a critical stabilizing role in the lumbar spine and is frequently atrophied or dysfunctional in patients with chronic low back pain.
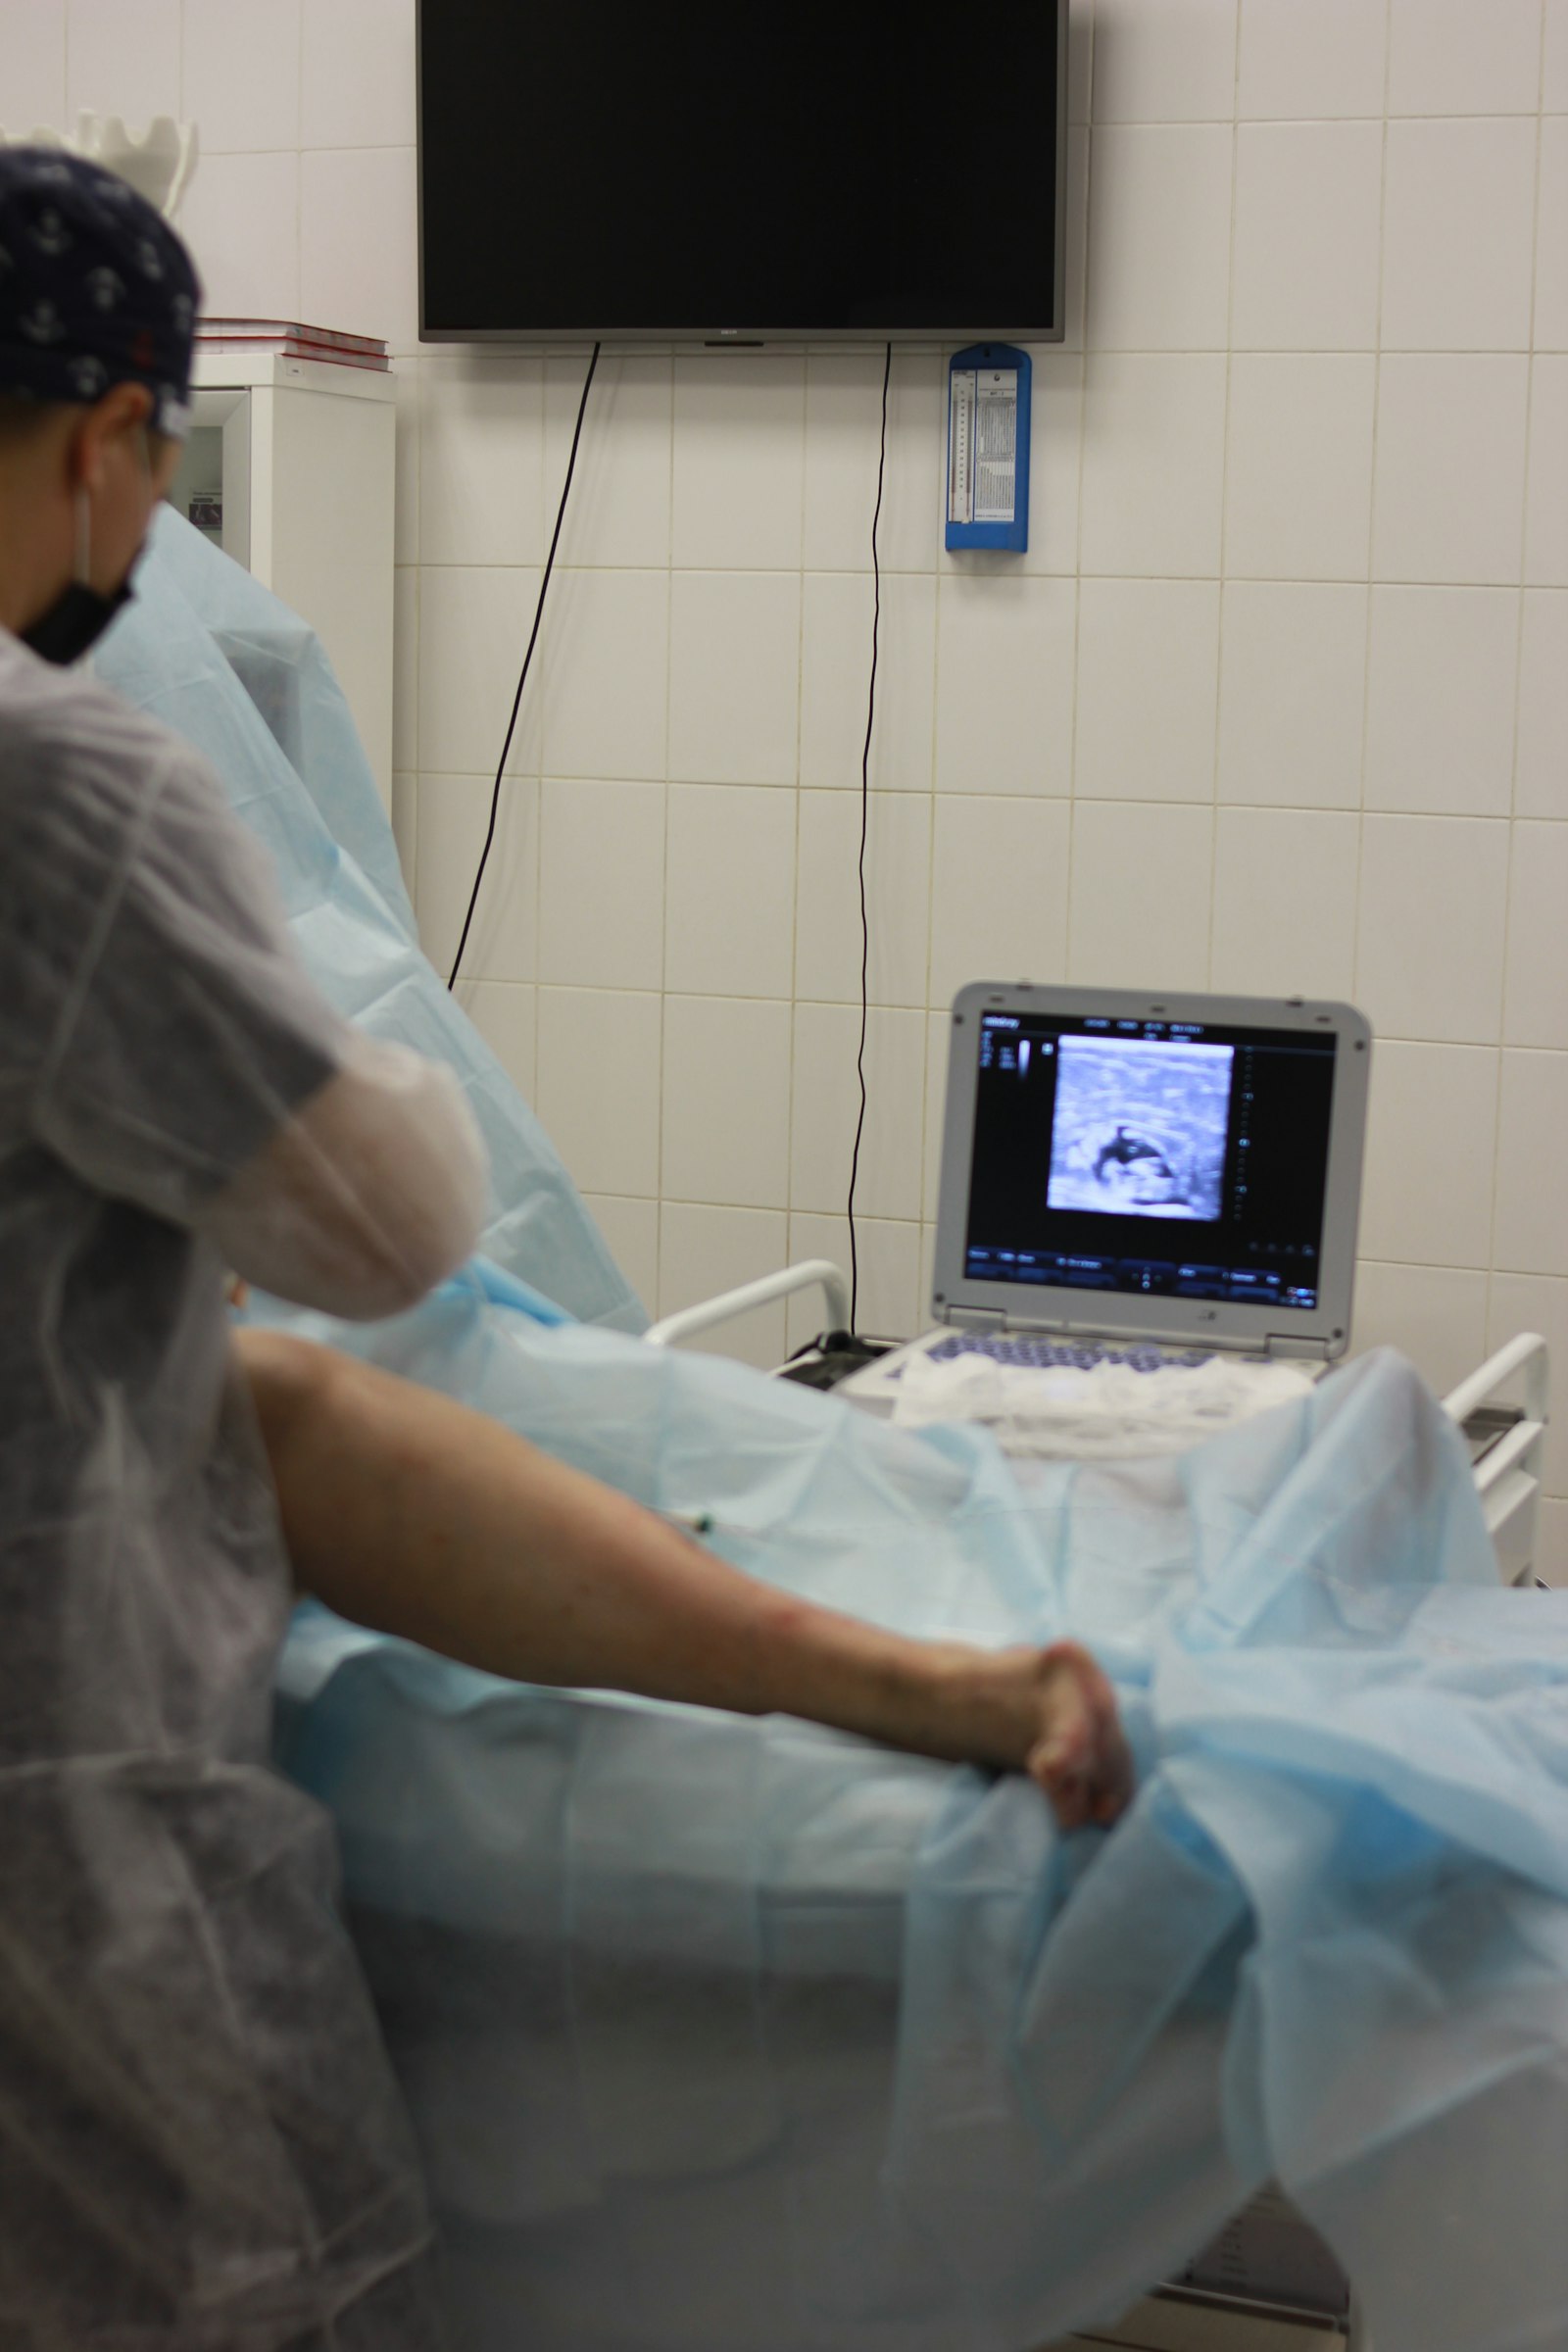
Under real-time ultrasound guidance, an experienced practitioner can navigate a single needle through sequential positions — from the transverse process, along the facet capsule, to the medial branch nerve, and ultimately to the lamina/multifidus interface — through one skin entry point. The clinical advantage of this approach is meaningful: fewer needle passes, shorter procedure time, and a continuous real-time view of needle position relative to target structures and surrounding anatomy.
Why Ultrasound Guidance Matters Here More Than Almost Anywhere
For peripheral joint injections, the clinical consequences of an off-target needle placement are usually limited — the injection may be less effective, but major complications are uncommon. For lumbar spine procedures, precision is more consequential. The proximity of neural structures, vascular anatomy, and the spinal canal itself makes real-time imaging not just preferable but, in the hands of a skilled practitioner, the appropriate standard.
Musculoskeletal ultrasound — when used by someone who has spent years developing both diagnostic and procedural proficiency — provides a live picture of soft tissue and bony anatomy that fluoroscopy cannot replicate for this purpose. It shows muscle planes, fascial layers, and real-time needle tip position in a way that informs moment-to-moment clinical decisions during the procedure itself, not just the initial targeting.
This is meaningfully different from ultrasound as a general positioning tool. The distinction is between a practitioner who uses ultrasound to find the general neighborhood, and one for whom the real-time image is the primary guidance modality throughout the procedure.
What the Evidence Currently Shows
Research on PRP for lumbar facet joint pain and medial branch pathology is earlier-stage than the literature on knee or shoulder applications. Preliminary studies show encouraging signals, and the mechanistic rationale — that concentrated growth factors can modulate inflammation and potentially support tissue repair in degenerated spinal structures — is consistent with the evidence base for PRP in other musculoskeletal applications. This remains an area of active investigation, and it is not appropriate to represent the current evidence as equivalent to the more established peripheral joint literature. What the evidence does support is that ultrasound-guided technique substantially reduces injection variability, which is a prerequisite for meaningful outcomes research in this area.
Who May Be Appropriate for This Approach
Patients who may be candidates for lumbar spine PRP evaluation include those with:
- Diagnosed lumbar facet syndrome or facet-mediated pain
- Chronic low back pain that has not responded to physical therapy, anti-inflammatory management, or conventional injections
- A preference for regenerative rather than destructive interventional options (e.g., alternatives to radiofrequency ablation)
- Imaging findings consistent with structural sources of pain, rather than symptoms attributable to disc herniation, spinal stenosis, or other pathologies requiring different management
In our practice, many of the patients referred for lumbar spine PRP evaluation have already been through a course of physical therapy and at least one round of facet or epidural steroid injections that gave only short-lived relief. Candidacy for any spinal orthobiologic procedure requires thorough clinical evaluation, diagnostic imaging review, and a shared decision-making conversation about realistic expectations. This is not a treatment for undiagnosed back pain.
When Surgery May Be More Appropriate
For patients with significant spinal stenosis, instability, disc herniation causing radiculopathy, or structural pathology that has not responded to conservative and interventional management, surgical evaluation is the appropriate path. PRP is not a substitute for a spine surgical consultation when that consultation is clinically indicated.
Limitations: What the Evidence Does Not Yet Show
Ultrasound-guided technique reduces procedural variability, but it does not by itself prove that PRP works for every lumbar spine condition.
- Research on PRP for lumbar facet and medial-branch pathology is earlier-stage than the literature for knee or shoulder applications, and larger controlled trials are still needed.
- This approach is not appropriate for disc herniation with radiculopathy, spinal stenosis, instability, or other pathology that may require a different treatment path.
- Technique alone does not guarantee results; outcomes still depend on accurate diagnosis, patient selection, and individual response.
- This article cannot determine whether lumbar PRP is appropriate for any individual reader — that requires clinical evaluation and imaging review.
Dr. Tortland's Perspective
The lumbar spine is one of the more technically demanding targets in musculoskeletal ultrasound-guided practice — and one of the more rewarding when it's done well. The ability to reach multiple structures through a single entry point isn't just a technical nicety; it changes what's clinically possible for patients who have facet-mediated pain layered on top of paraspinal muscle dysfunction. I've used musculoskeletal ultrasound clinically since 2008. For spinal work, I can't imagine practicing without it.